









Time to read: 8 min
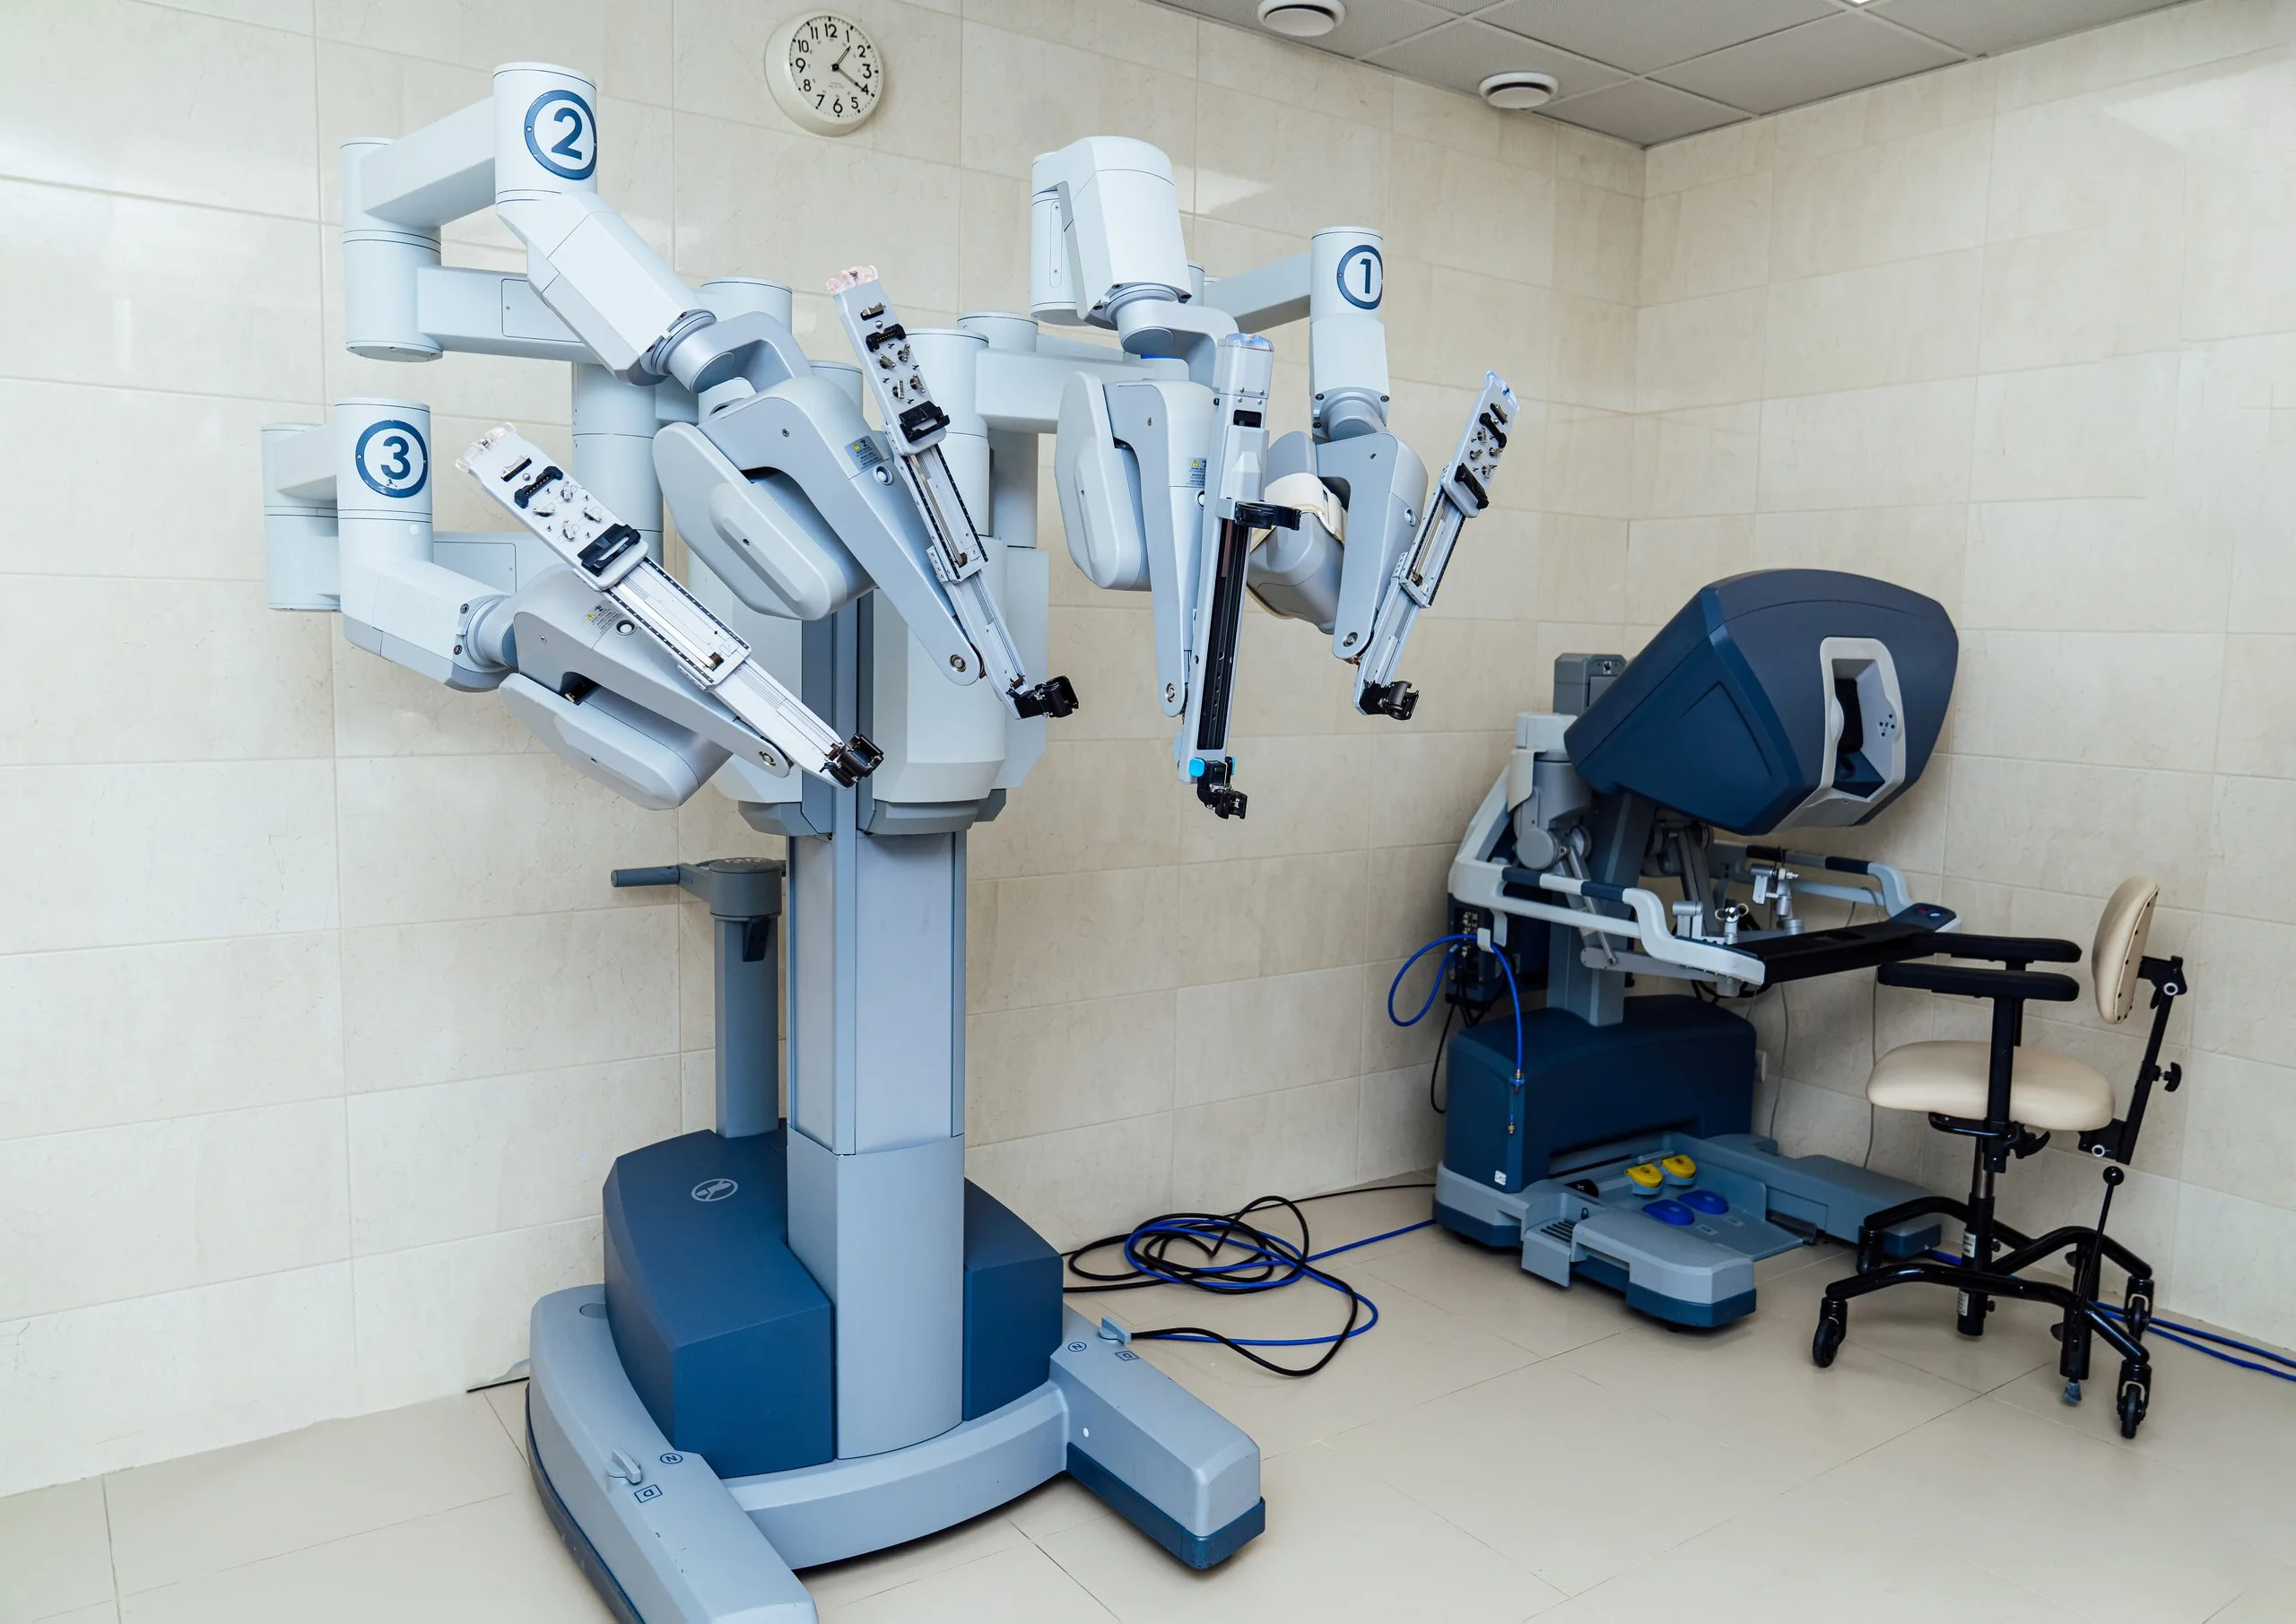
A surgical robotic system can consist of thousands of individual parts. The instruments that enter the patient’s body need to withstand dozens to hundreds of sterilization cycles, operate through submillimeter ranges of motion, and apply tissue-contact forces that can be fractions of a newton. The housing components that contain the drive mechanisms are manufactured to tight, function-driven tolerances. This is what surgical robotics hardware manufacturing actually looks like.
Surgical robotics hardware manufacturing is the production of precision components for robotic surgery systems and parts that must meet medical device biocompatibility and sterilization requirements, hold the tight actuator tolerances that robotic surgery demands, and come with the lot-specific material certifications and ISO 13485 documentation that FDA-regulated programs require.
It sits where two demanding manufacturing verticals meet: medical devices and precision robotics. But it’s more than one industry’s requirements stacked on top of the other’s. Engineers coming from industrial robotics often underestimate FDA documentation and biocompatibility requirements. Engineers from conventional medical device backgrounds may underestimate the demands of precision actuator tolerances and repeated sterilization cycling. The combination of requirements creates a distinct category of manufacturing with its own specifications, materials, and quality obligations.
What Sets Surgical Robotics Hardware Apart
Three characteristics define this category and distinguish it from both conventional medical devices and industrial robotics.
Tolerance and biocompatibility
An actuator housing for an industrial robot commonly holds bearing seats to H7 tolerances for engineered fits. Surgical robot components are manufactured from biocompatible materials, finished to survive repeated sterilization without degradation, and documented with material traceability required for FDA-regulated devices. Missing any one of these requirements can cause a part to fail supplier qualification or validation.
Miniaturization
Laparoscopic and endoscopic instruments typically operate through 5- to 12-mm-diameter ports. The actuator mechanisms, cable routing features, and articulation joints inside these instruments are machined at a scale where a precision 0.025mm positional tolerance represents a meaningful fraction of the feature size. The manufacturing challenge is fundamentally different from a 120mm housing, even when the nominal tolerance values look similar.
Sterilization cycling
Surgical instruments are sterilized by autoclaving (typically 121–134°C for 3–18 minutes) or by ethylene oxide gas, many times over their service life. Materials and surface treatments must survive this without dimensional change, surface degradation, corrosion, or release of cytotoxic compounds. Biocompatibility in a single-use context is not the same as compatibility with repeated autoclave cycling.
Materials for Surgical Robotic Components
Titanium (Ti-6Al-4V and Grade 23 ELI)
Titanium Ti-6Al-4V (Grade 5) is the primary structural material for surgical robotic components that require a high strength-to-weight ratio, corrosion resistance, and established biocompatibility. Titanium can be machined to tight tolerances with appropriate tooling, though its low thermal conductivity and tendency to work-harden require more careful process control than aluminum or stainless.
Grade 23 Ti-6Al-4V ELI (Extra Low Interstitial) has tighter limits on oxygen, nitrogen, carbon, and iron content, which improves fracture toughness and fatigue performance. For structural components that must withstand high-cycle fatigue loading, Grade 23 is often specified as a conservative choice even when Grade 5 would meet the mechanical requirements on paper.
316L Stainless Steel
316L stainless steel is widely used for surgical instrument components in corrosive biological fluid environments. Passivation per ASTM A967 is typically required after machining and welding, with documentation requirements that are more stringent than industrial passivation. Electropolishing per ASTM B912 is specified for high-hygiene components: it removes the outermost surface layer including embedded iron particles, producing a smooth surface (Ra 0.4 µm or better) that is easier to clean and sterilize. Specify electropolishing for product-contact and body-contact stainless components.
PEEK
PEEK is the engineering plastic of choice for MRI-compatible, electrically isolating, or chemically resistant structural components. It survives repeated autoclave sterilization without dimensional change or degradation, which many engineering plastics cannot. Specify medical-grade PEEK with supplier documentation, not general-purpose industrial PEEK, to ensure traceability and regulatory documentation. PEEK is typically injection molded for higher volumes, and is also machinable for tighter tolerances, if necessary. Biocompatibility of PEEK components in patient-contact applications must be verified per ISO 10993 for the specific part geometry, surface condition, and contact duration. Material grade alone does not establish biocompatibility.
Aluminum
Aluminum is appropriate for non-patient-contact structural components and console housings where weight is a concern and direct tissue contact doesn’t occur. Type III hard anodize (MIL-PRF-8625) provides a wear-resistant surface for bearing interfaces. Anodized aluminum is not suitable for instrument components that go through steam autoclave sterilization because alkaline cleaning agents and repeated steam exposure degrade the porous anodized layer over repeated cycles.
Tolerances and Geometric Requirements
Surgical robotic components often sit toward the tighter end of what CNC machining can reliably produce, but most features on a part don’t need to. The practical approach is to hold standard tolerances wherever function allows and apply tighter, drawing-specific tolerances only to the features that drive performance. Over-tolerancing non-functional features adds inspection time and cost without improving the device.
Bearing seats and drive alignment.
Bearing seat bores are typically toleranced to ISO H6 or H7 fits, depending on the bearing series and the bearing manufacturer’s recommendation. Alignment between input and output bearing bores is better controlled with GD&T (runout, position, or coaxiality callouts) than with size tolerances alone. Required values depend on the bearing type, the drive’s speed and load, and how much friction and noise the design can accept.
Cable routing and tension features.
Cable path geometry affects mechanical advantage and force transmission, so the position and surface finish of guide features influence friction, hysteresis, and cable wear. Dimensional variation at the housing level shows up as variation in force and motion at the instrument tip. Tolerance these features by function, using position callouts referenced to datums that mirror how the part is assembled.
Articulation joints
Pivot pin bores, joint surfaces, and clearance fits set the joint’s backlash, which affects positional accuracy and repeatability at the instrument tip. Build an explicit tolerance stack-up for the joint rather than leaving it to manufacturing variation.
Surface finish and corner radii
Patient-contact features are typically specified by Ra, often with an electropolished finish on stainless components to improve cleanability. The final values and minimum internal radii are usually set by the device manufacturer’s cleaning and reprocessing validation. Crevices and surface irregularities that trap biological material are design failures in surgical instruments, not cosmetic issues.
Coatings and dimensional change
Finishes alter dimensions. Hard anodizing, for example, grows outward by roughly half its coating thickness per surface, which matters for bearing seats and other tight fits. Specify whether tolerances apply before or after finishing, and mask critical bores when needed.
Designing for Sterilization Compatibility
Sterilization compatibility is a design requirement, not a material selection afterthought. The following decisions determine whether a component survives tens to hundreds of sterilization cycles, depending on the device.
Material and finish selection for autoclave cycling
316L stainless (passivated or electropolished), titanium alloys, and PEEK survive repeated autoclaving without degradation, as do some other high-performance polymers such as PPSU and PEI. Many other engineering plastics do not. Type II and Type III anodized aluminum are not suitable for steam autoclave sterilization of instrument components.
Sealed vs. serviceable assemblies
Sealed assemblies must prevent fluid ingress during sterilization, using seals rated for the cycle’s temperature, pressure, and vacuum swings. Fully hermetic enclosures can rupture under these swings, so some designs instead let steam penetrate and drain. Components disassembled for cleaning must allow tool-free or common-tool disassembly, with internal surfaces accessible for manual cleaning and inspection.
Galvanic and crevice corrosion at interfaces
Dissimilar metal interfaces in a saline and biological fluid environment create galvanic corrosion risk, and tight crevices at joints and interfaces can drive crevice corrosion. Use electrochemically compatible metal combinations, minimize crevices, or electrically isolate dissimilar metals with PEEK or ceramic insulators where necessary.
Thread form
Fine-pitch threads trap biological material. Where possible, use coarser pitches on external features, or replace threaded interfaces with bayonet or quarter-turn systems that clean more reliably.
Quality Documentation for Surgical Robotics Programs
Surgical robotic component suppliers are typically held to QMSR-aligned requirements through OEM supplier controls. The Quality Management System Regulation documentation requirements go well beyond what most general CNC machine shops maintain as standard practice.
Lot-specific material certifications are typically required for metals: heat number, chemical analysis, and mechanical properties traceable to a specific production lot.
First Article Inspection (FAI) documentation should cover critical drawing requirements on first production parts, with CMM reports or hand measurement records and a bubble diagram of the drawing. FAI is usually repeated after any significant process change, not only at initial production.
Certifications of conformance are typically required for surface treatments: passivation bath chemistry and process parameters, electropolish records, anodize bath certifications. These processes must be documented and repeatable, not performed informally.
Surgical robotic component suppliers are typically held to ISO 13485-aligned quality requirements through OEM supplier controls. These are requirements that flow from the device manufacturer’s QMSR obligations under the FDA’s Quality Management System Regulation (effective February 2026). Verify the scope of the certification matches the processes being performed. A machine shop certified for general machining is not automatically certified for medical device component manufacturing.

Read our TransMed7 case study to learn how Fictiv helped save time and cost on development for their biopsy devices.
Ready to Build?
Surgical robotics hardware leaves little room for guesswork. Material choices, tolerances, finishes, and documentation all have to line up before a part passes validation. Fictiv’s manufacturing network supports CNC machining, injection molding, and finishing for medical and robotics applications, with design for manufacturability (DFM) feedback early in the process.
Upload your CAD files to get an instant quote and DFM feedback, or talk with a Fictiv manufacturing expert about your materials, tolerances, and documentation requirements.
Talk to a Fictiv expert about your project, or upload your parts to start a free quote.

